Contents
Elliot had been, in Antonio Damasio’s words, “a good husband and father, had a job with a business firm, and had been a role model for younger siblings and colleagues.” Then a tumour the size of a small orange grew above his eye sockets and pressed on both frontal lobes from below.
Surgeons removed it together with the damaged tissue of the lower, middle part of the frontal lobes. Elliot recovered. His IQ was “in the superior range”, his scores on a standard personality inventory were normal, and he had “a flawless memory for his life story” (Damasio, 1994, pp. 35–44).
And he could no longer run his life. At work, given documents to sort, “he might spend a whole afternoon deliberating on which principle of categorization should be applied: Should it be date, size of document, pertinence to the case, or another? The flow of work was stopped” (p. 36).
He lost his job, then his savings in a doomed business venture, then his marriage; a second marriage, which his family opposed, also ended in divorce (p. 37).
In one test, a psychologist on Damasio’s team asked him to come up with ways to act in social dilemmas. Elliot produced a long list of reasonable options, smiled, and added: “And after all this, I still wouldn’t know what to do!” (p. 49).
Damasio summed up Elliot’s condition in six words: “to know but not to feel” (p. 45). His book Descartes’ Error (1994) built a theory on that phrase.
Emotion, it says, is not the enemy of good decisions but part of the machinery that makes them, and the part that was missing in Elliot was a signal from the body. This post goes through the theory, the experiment that made it famous, the experiments that challenged it, and what is left.
Two patients
Elliot was not the first patient with this kind of damage to become famous.
On 13 September 1848, near Cavendish, Vermont, a railway foreman named Phineas Gage was packing explosive into a drill hole when the charge went off and drove his tamping iron, “three feet, seven inches in length, one and one quarter inch in diameter”, weighing 13¼ pounds, through his left cheek and out of the top of his head[1].
He survived and was talking within minutes. His physician, John Harlow, later described the change: Gage became “fitful, irreverent, indulging at times in the grossest profanity”, so that “his friends and acquaintances said he was ‘no longer Gage’“[2].
Gage is the textbook case of the frontal lobes and personality, and the textbook version is too simple in two ways. First, he recovered more than it suggests.
By Harlow’s own account he worked in a livery stable and then spent nearly eight years in Chile driving stagecoaches, six horses and a heavy load, a job that demands planning and reliability; the historian Malcolm Macmillan, who spent decades on the case, concluded that he “eventually made a surprisingly good psychosocial adaptation to his injury”[3].
Second, his damage may not have been what Damasio’s case needed. In 1994 Hanna Damasio and colleagues reconstructed the path of the iron from measurements of the skull and concluded that it damaged the ventromedial prefrontal cortex on both sides[4].
Later reconstructions from CT scans of the skull itself found the damage limited to the left frontal lobe[5, 6].
Elliot is better documented. In the research literature he is patient EVR, an accountant at a home-building firm, whose “‘measurable’ intelligence was superior, and he was therefore considered a ‘malingerer’” before anyone understood what had happened to him[7].
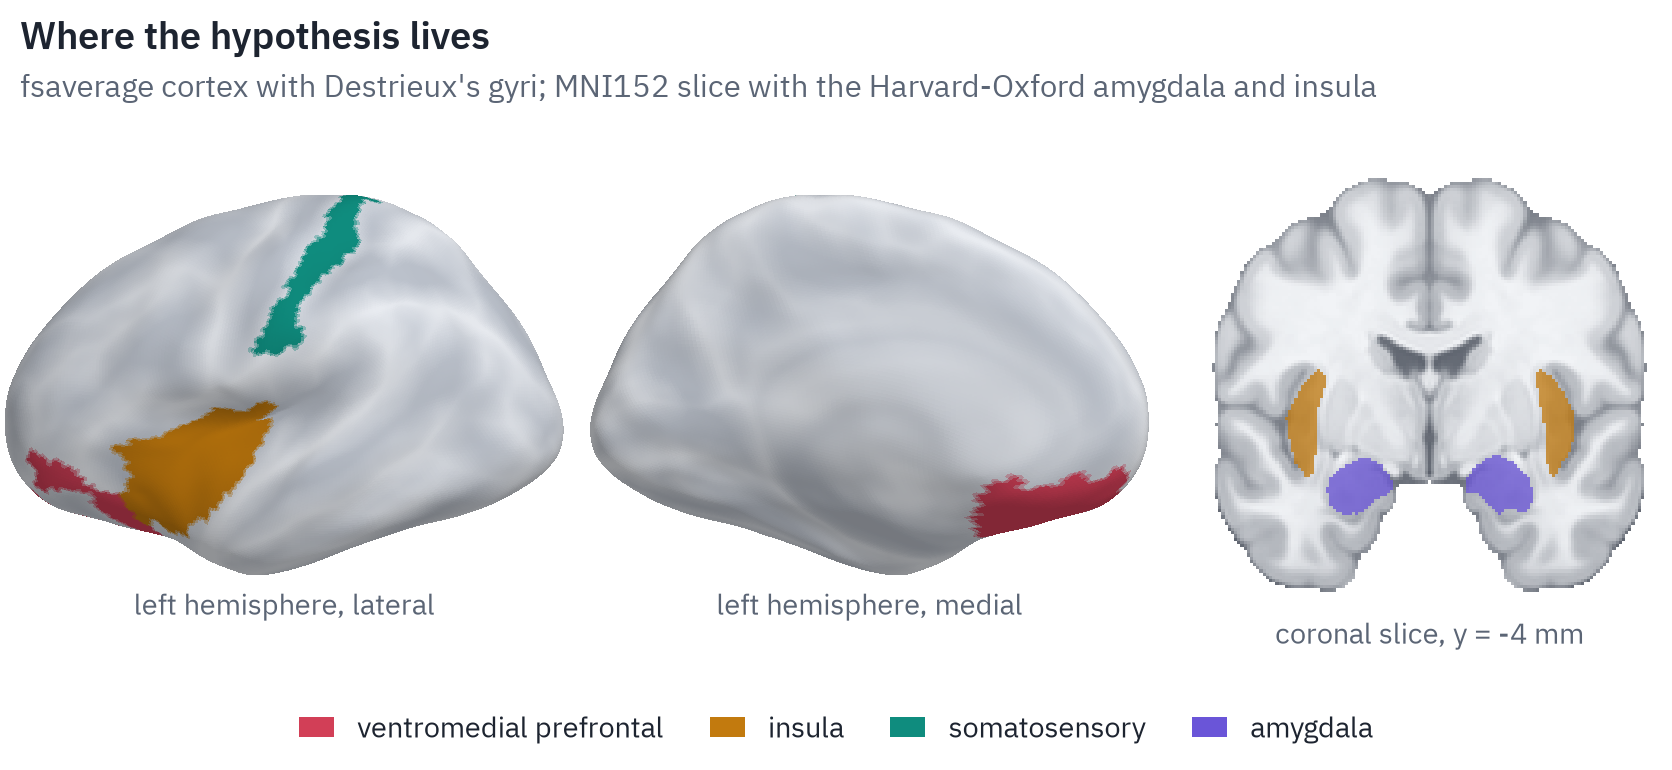
The region at the centre of the story is the ventromedial prefrontal cortex (vmPFC), the lower, inner surface of the frontal lobes, just above the eyes:
The hypothesis
Damasio’s question was what the vmPFC contributes that IQ tests do not measure. His answer is the somatic marker hypothesis[8].
When we consider an option, the brain does not only compute its consequences. It also re-evokes the bodily state that similar situations produced in the past: a tightening, a flicker of something like fear or relief. That state marks the option.
A bad marker works as “an alarm signal”, a good one as “an incentive signal”, and when the process runs below awareness it is a “biasing signal” that tilts the choice before reasoning finishes.
Key point
The vmPFC, on this view, stores the links between kinds of situations and the bodily states they led to, and without it a person can still reason about options but nothing makes one of them feel worse than another. Elliot’s afternoon spent choosing a filing principle is what deciding looks like when every option weighs the same.
The word somatic, from the Greek sōma, body, is literal, but not in the way it is often retold. The signals do not have to travel to the body and back. Damasio describes two routes:
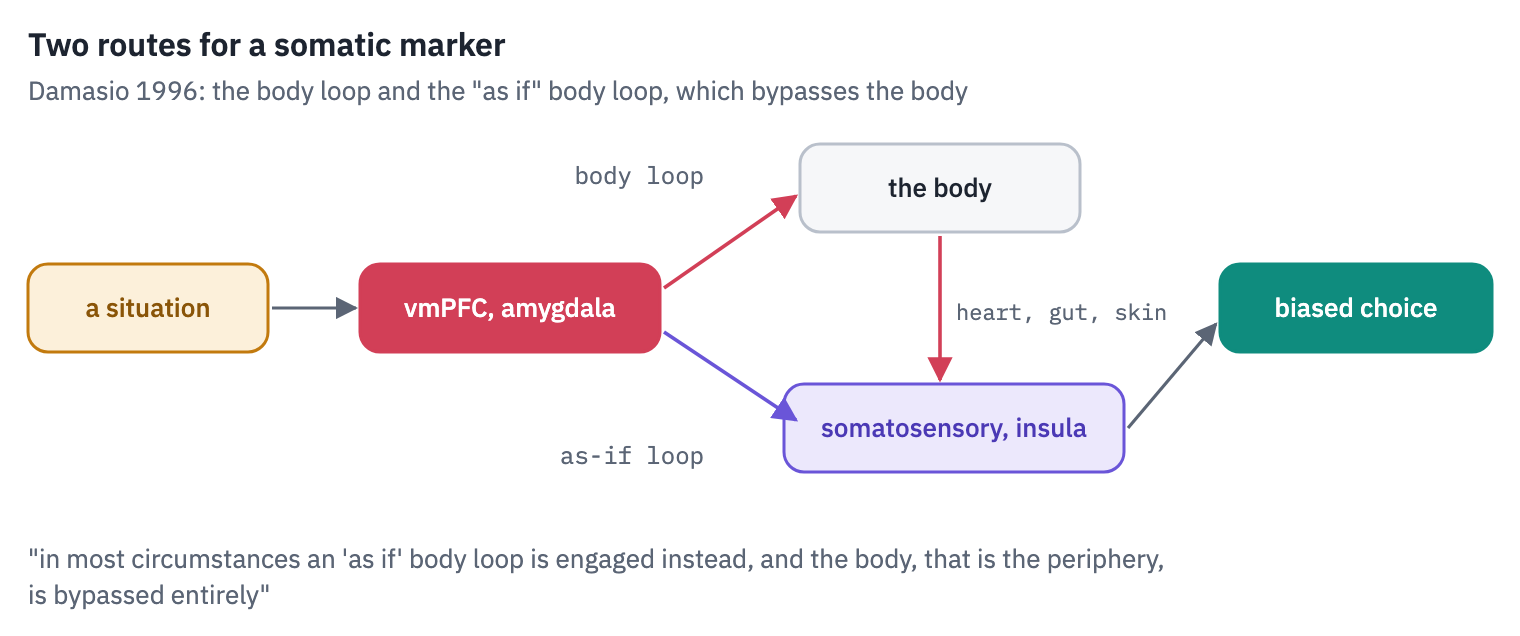
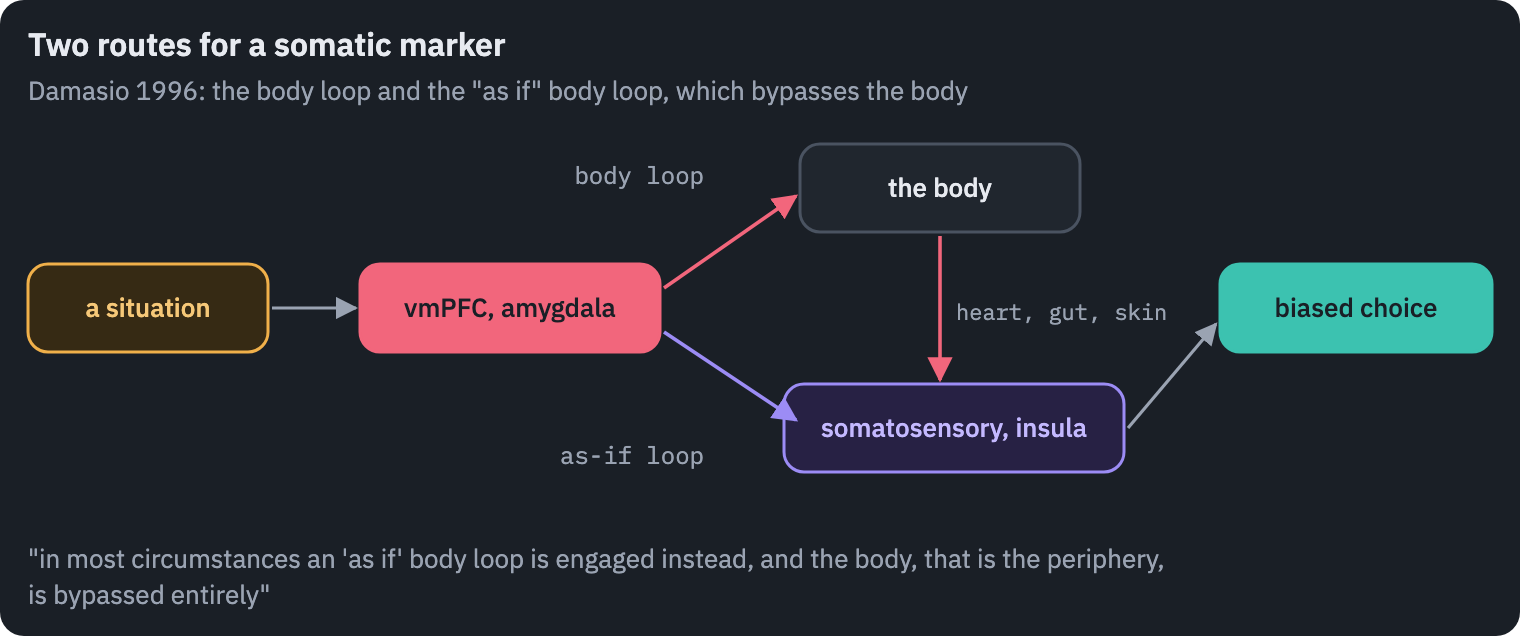
In the body loop, the situation changes the state of the body, heart rate, breathing, the gut, the skin’s sweating, and the somatosensory cortex and the insula register the change.
In the as-if body loop, the vmPFC signals those cortical maps directly and they adopt the pattern the body would have produced, “the body being bypassed”.
Damasio thought the second route is the usual one: “in most circumstances an ‘as if’ body loop is engaged instead, and the body, that is the periphery, is bypassed entirely.”
The idea has an ancestor. In 1884 William James argued that “we feel sorry because we cry, angry because we strike, afraid because we tremble, and not that we cry, strike, or tremble, because we are sorry, angry, or fearful”[9].
Walter Cannon objected in 1927 that bodily changes are too slow and too much alike across emotions to be the source of feelings, and that animals whose viscera were cut off from the brain still showed emotional behaviour[10].
Damasio’s version keeps James’s insight and answers part of Cannon’s objection with the as-if loop. It also separates two words that everyday language mixes.
Emotions are action programs, chains of bodily responses triggered by a situation. Feelings are the experience of those changes, “mental experiences, closely connected to activity in certain brain regions capable of mapping body states”[11].
The card game
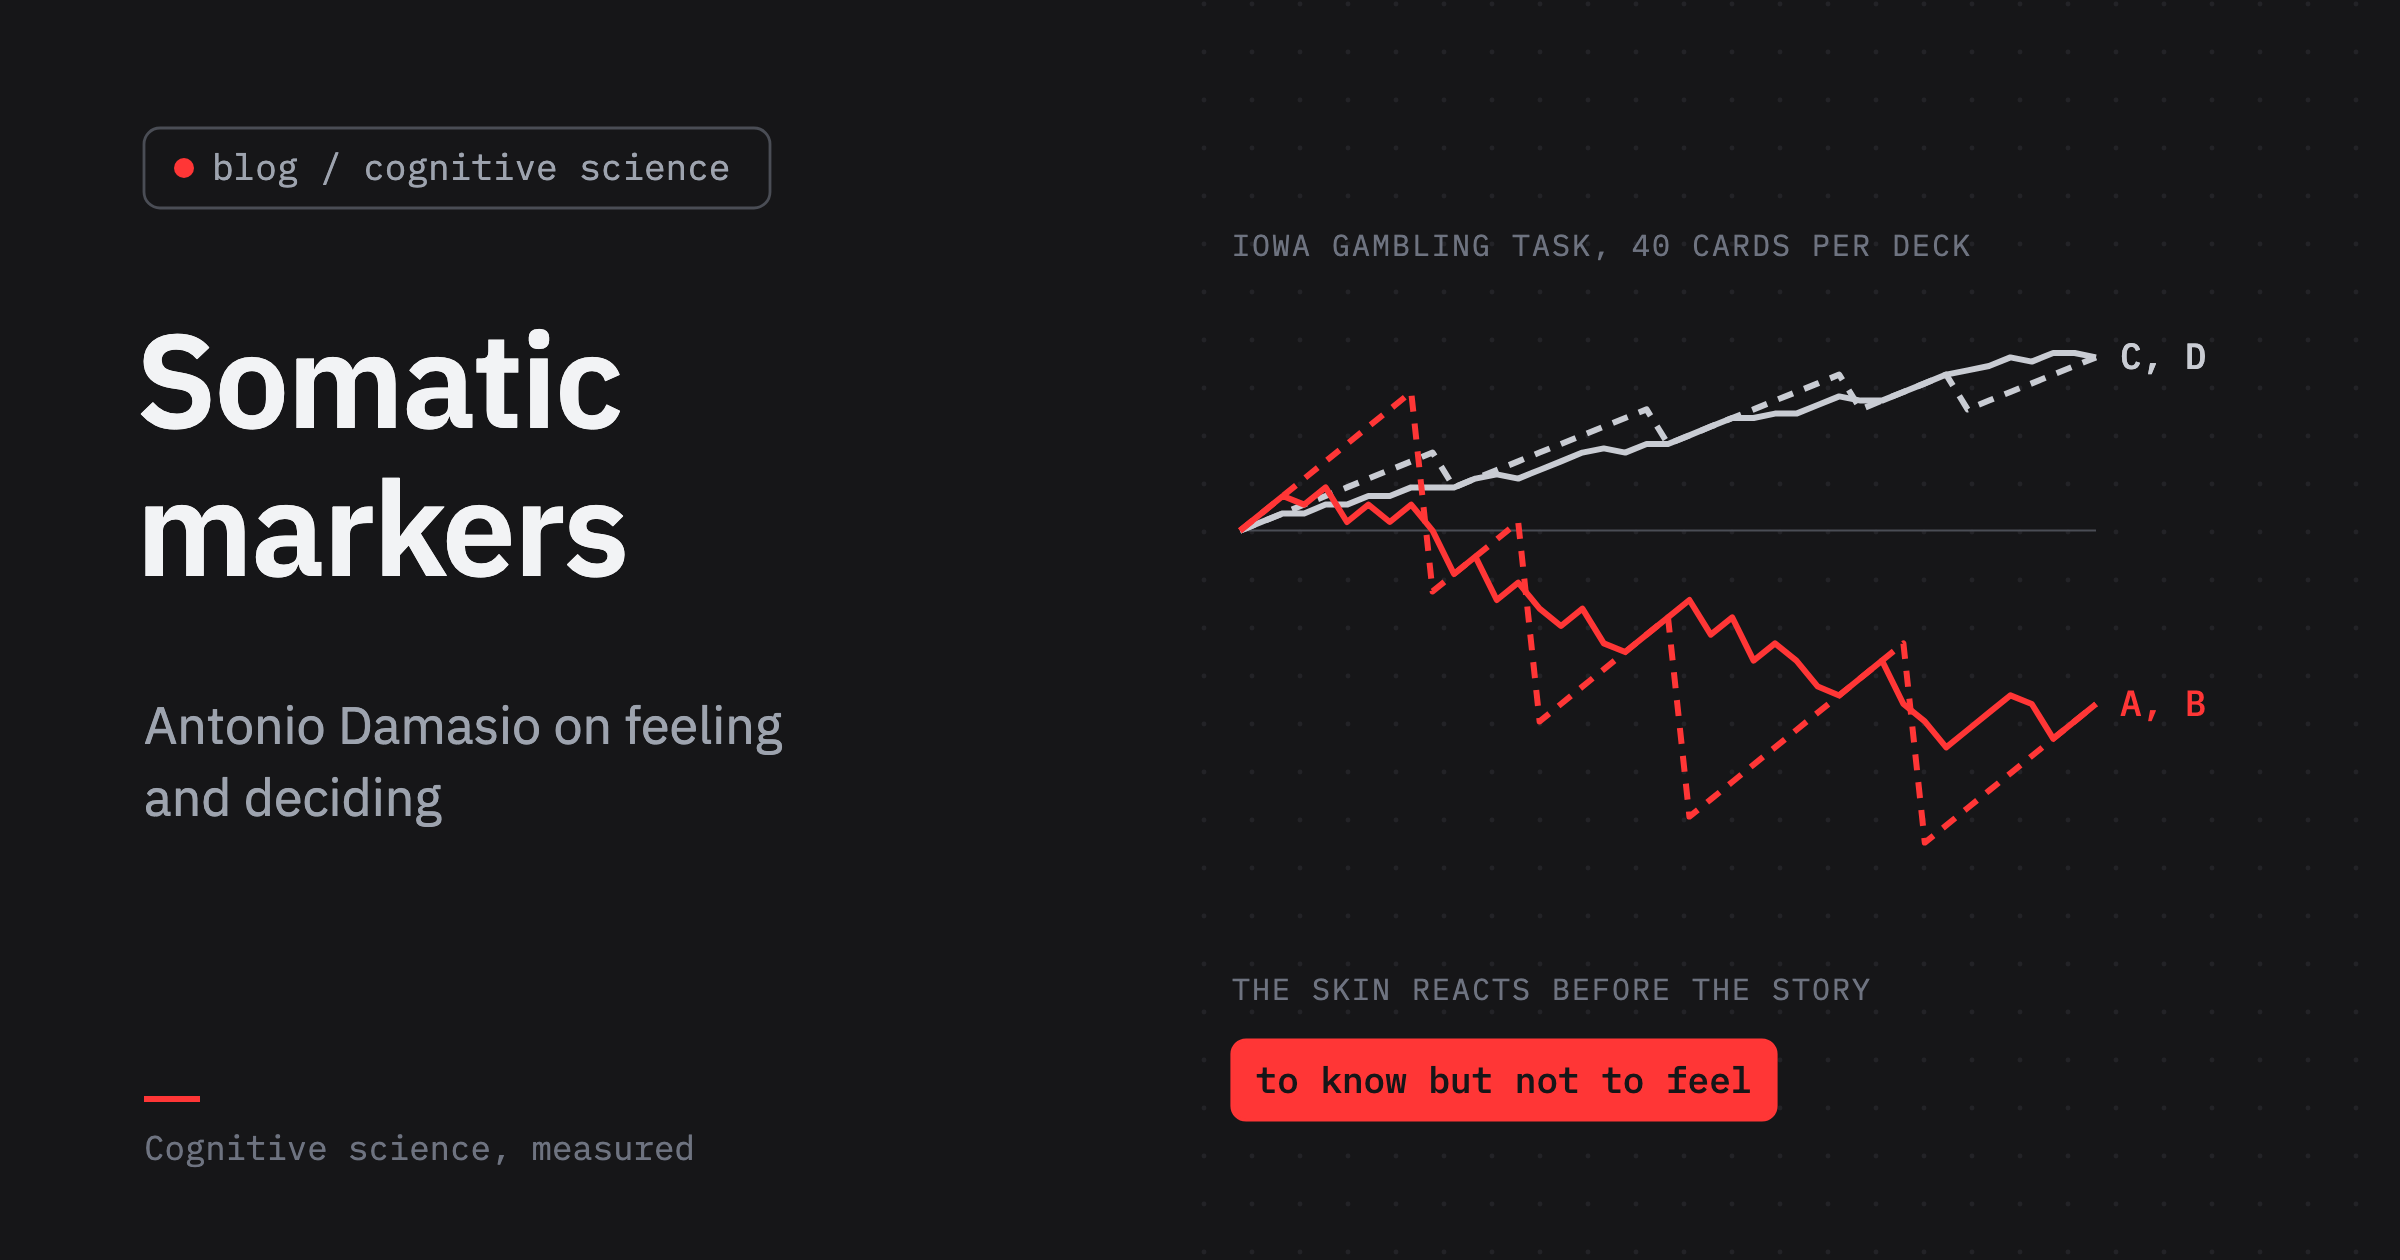
To test the hypothesis, Antoine Bechara, working in Damasio’s lab at the University of Iowa, built what is now called the Iowa Gambling Task[12]. The player gets a loan of $2,000 in play money and four decks of cards.
Each card pays a reward; some cards also take a penalty. The player is not told the rules and does not know the game stops after 100 cards. The decks are rigged:
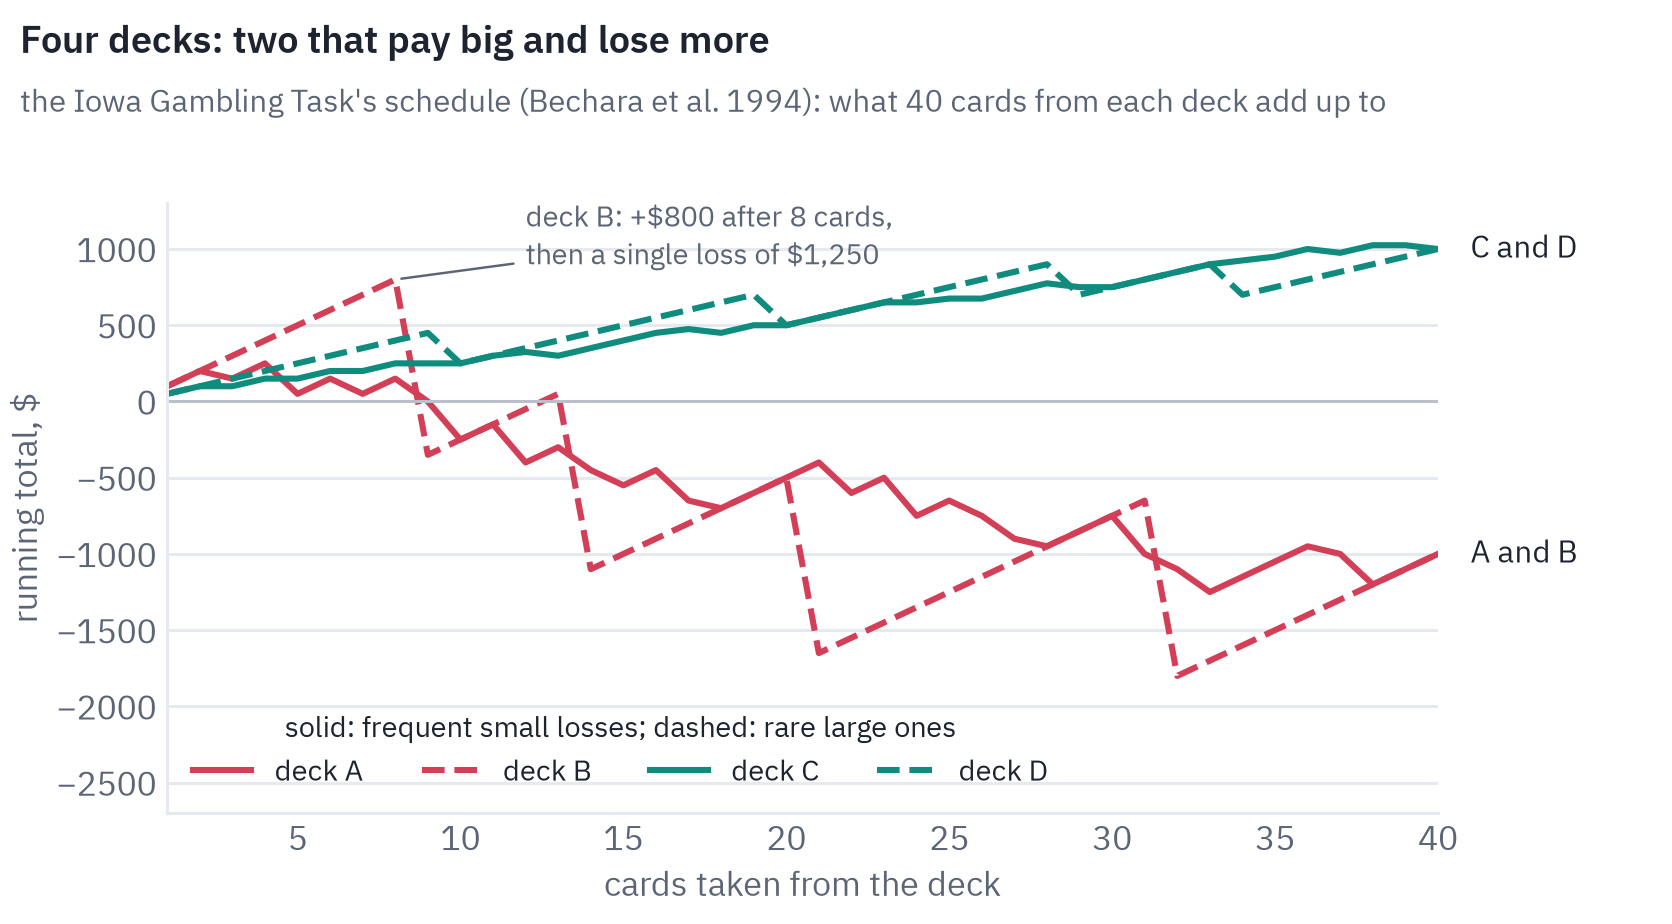
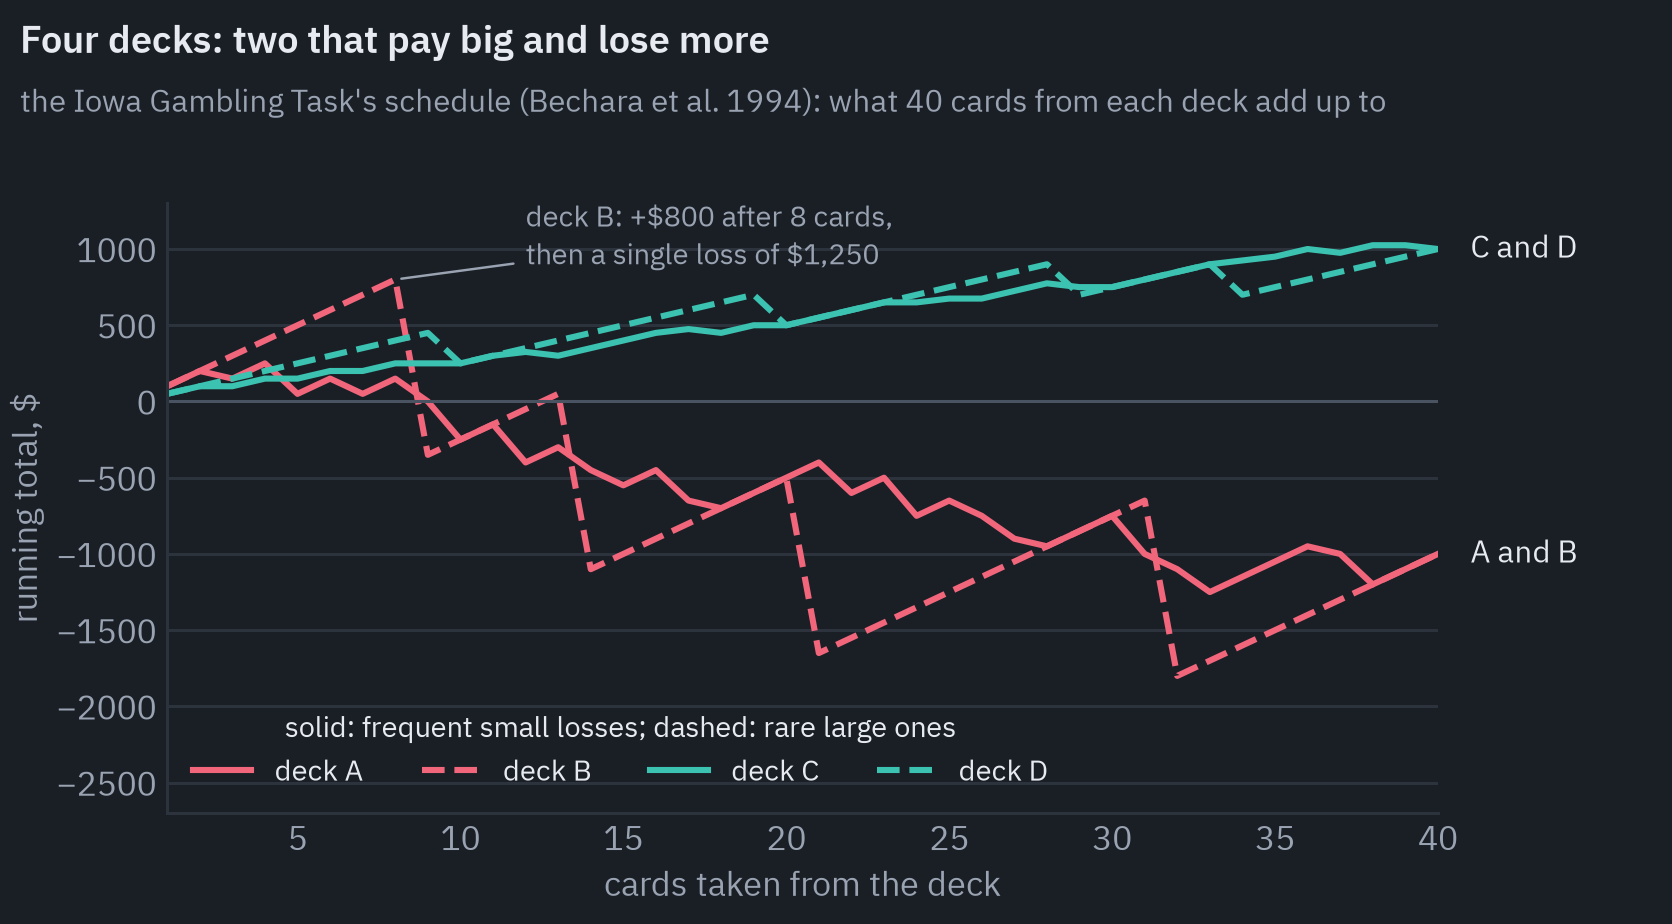
Decks A and B pay $100 a card, decks C and D $50. But A and B also take larger penalties, and every ten cards from them lose $250 on balance, while ten cards from C or D win $250. The two bad decks differ in how they punish.
Deck A takes frequent losses of a few hundred dollars. Deck B pays $100 nine times in a row, $800 ahead by the eighth card, and then takes $1,250 at once. Learning to avoid A and B requires adding up experiences that point the other way at first.
Healthy players drift toward C and D. Patients with vmPFC damage kept choosing A and B to the end, and when EVR was tested again 24 hours, a month and six months later, his “performance did not change”. The game reproduced in the lab what Elliot did in life.
Before knowing
The experiment that made the hypothesis famous came three years later[13]. Ten healthy participants and six patients with damage to the vmPFC on both sides played the game while their skin conductance was recorded: a measure of sweating, which rises with arousal.
After the 20th card, and every ten cards after that, the game was paused and they were asked what they knew about it and how they felt about it.
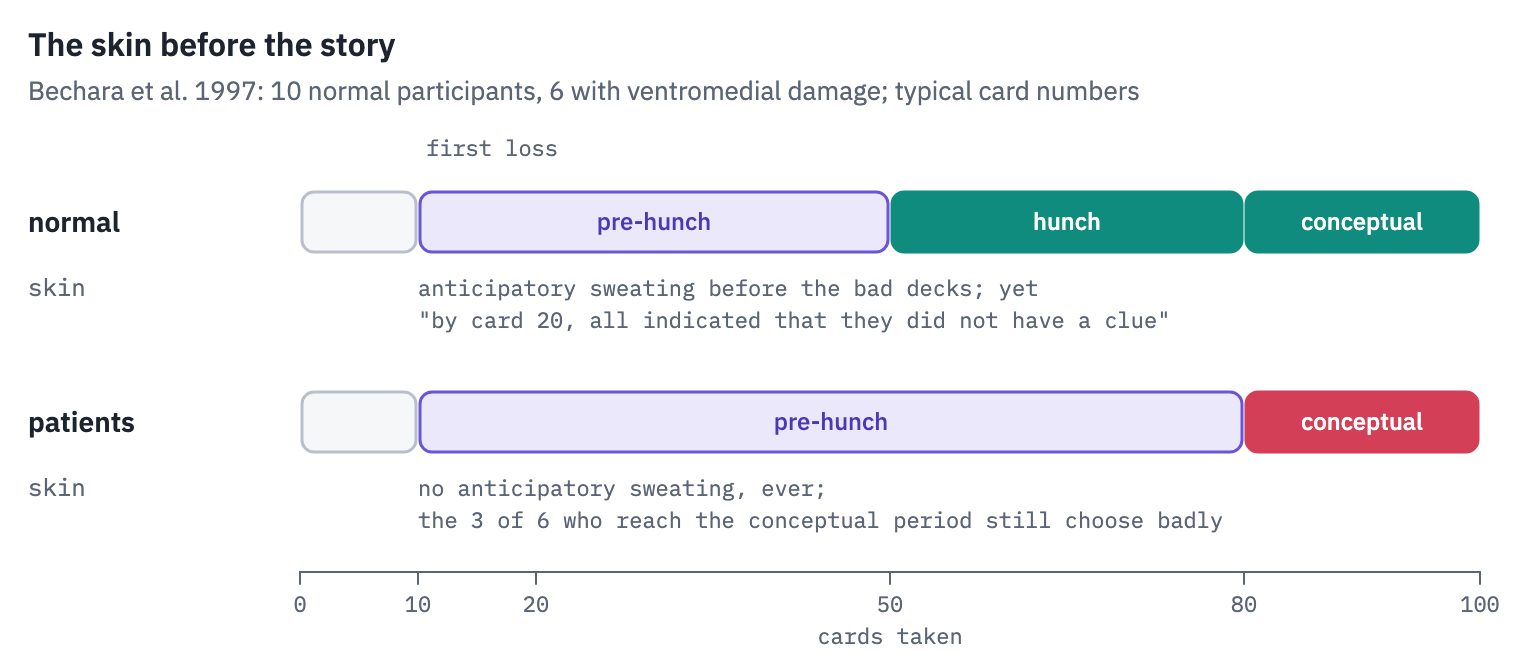

The healthy players went through four periods. After the first losses their skin began to respond before they picked a card from a bad deck, an anticipatory reaction that the patients never developed. Yet “by card 20, all indicated that they did not have a clue about what was going on.”
Around card 50 they reported a hunch, a feeling that some decks were riskier. Around card 80, seven of the ten could say which decks were bad and why.
The patients’ results were stranger. Three of the six worked out which decks were good and which bad, and still chose badly: “The patients failed to act according to their correct conceptual knowledge.”
The paper’s abstract concluded that “in normal individuals, nonconscious biases guide behavior before conscious knowledge does.”
It is a beautiful result, and the paper itself contains its first caveat. During the pre-hunch period, the healthy players did choose more often from the good decks, but in a footnote the authors note that “the difference was not statistically significant.”
The evidence against
Over the next decade the hypothesis drew careful criticism, most of it about the gambling task.
People knew more than they were asked. Tiago Maia and James McClelland replayed the experiment with a more detailed questionnaire and found that “participants report knowledge of the advantageous strategy more reliably than they behave advantageously”[14].
Conscious knowledge appeared at least as early as good choices, so there was no need to invoke unconscious bodily biases to explain them, though they did not show that such biases are absent.
The sweating may track risk, not badness. In the standard game the bad decks are also the ones with the largest swings. Ian Tomb and colleagues built a version in which the good decks had the largest swings, and anticipatory skin responses followed the swings, not the outcome[15].
People without bodily feedback play normally. Patients with pure autonomic failure, whose nervous system no longer produces the bodily changes the body loop needs, “were unimpaired” on the gambling task; they did slightly better than controls[16]. The as-if loop can absorb this result, but it then becomes hard to say what observation could count against the theory.
The patients’ problem may be more specific. In the standard schedule the bad decks look good at first, so a player must reverse an early preference.
Lesley Fellows and Martha Farah found that vmPFC patients’ impairment “seems to be largely explained by an underlying reversal learning deficit”; with the cards shuffled so that the bad decks did not look good at first, the patients played like everyone else[17].
Healthy people are not as good as the story assumes. Many healthy players prefer deck B, attracted by its rare losses[18]; their choices are idiosyncratic and do not settle down over the game[19].
A meta-analysis of anticipatory skin responses across studies found “a significant, small difference” between good and bad decks, r = 0.10, and a likely publication bias[20].
Barnaby Dunn and colleagues reviewed the whole literature in 2006. Studies outside Iowa usually reproduce the patients’ behavioural deficit, they found, but the theory built on it “requires additional empirical support to remain tenable”[21].
What remains
The criticism hit the mechanism, not the observation. Damage to the vmPFC really does leave people intelligent and unable to run their lives, and the deficit shows up in the lab.
What is disputed is the claim that the missing ingredient is a signal from, or about, the body, and that it works below awareness. Elliot’s phrase still describes his condition; whether “feel” there means a bodily state, an expectation of value, or the ability to update one, is the open question.
Damasio’s own work moved on to that question. In his later books, Self Comes to Mind (2010), The Strange Order of Things (2018) and Feeling & Knowing (2021), feelings are the mind’s view of homeostasis, the body’s work of keeping itself within the range where it can live: “Feelings are mental experiences of body states”[22].
Other researchers locate that view in the insula, which A. D. Craig described as building a representation of “the material me”[23]; Damasio and colleagues answered with a patient whose insulae were destroyed on both sides and whose feelings were intact, and argued that feelings arise first in the brainstem[24].
Lisa Feldman Barrett proposes a different picture altogether, in which “emotions are constructions of the world, not reactions to it”: the brain predicts what its bodily sensations mean and categorizes them with learned concepts[25].
Measuring how well people perceive their own bodies turns out to be hard in its own right: in the common heartbeat-counting test, accuracy scores mostly reflect people under-reporting, and actual and reported heartbeats correlate at only r = 0.16[26].
The theory has also reached machines. In 2019 Kingson Man and Damasio asked what the field of AI rarely asks[27]:
Attempts to create machines that behave intelligently often conceptualize intelligence as the ability to achieve goals, leaving unanswered a crucial question: whose goals?
Kingson Man and Antonio Damasio
A reinforcement-learning agent maximizes a reward someone wrote down for it. A living thing has something at stake, its own continued existence, and Man and Damasio suggest that machines which maintain an internal state of their own, as bodies do, “might also acquire a source of motivation and a new means to evaluate behaviour, akin to that of feelings”.
Elliot, with his intact intelligence and his lists of options, is a fair picture of an agent that can compute everything and has no reason to prefer anything.
References
- Harlow, J. M. (1848). Passage of an iron rod through the head. Boston Medical and Surgical Journal, 39, 389–393. ↩
- Harlow, J. M. (1868). Recovery from the passage of an iron bar through the head. Publications of the Massachusetts Medical Society, 2, 327–347. ↩
- Macmillan, M., & Lena, M. L. (2010). Rehabilitating Phineas Gage. Neuropsychological Rehabilitation, 20(5), 641–658. ↩
- Damasio, H., Grabowski, T., Frank, R., Galaburda, A. M., & Damasio, A. R. (1994). The return of Phineas Gage: clues about the brain from the skull of a famous patient. Science, 264, 1102–1105. ↩
- Ratiu, P., Talos, I.-F., Haker, S., Lieberman, D., & Everett, P. (2004). The tale of Phineas Gage, digitally remastered. Journal of Neurotrauma, 21(5), 637–643. ↩
- Van Horn, J. D., et al. (2012). Mapping connectivity damage in the case of Phineas Gage. PLoS ONE, 7(5), e37454. ↩
- Eslinger, P. J., & Damasio, A. R. (1985). Severe disturbance of higher cognition after bilateral frontal lobe ablation: patient EVR. Neurology, 35(12), 1731–1741. ↩
- Damasio, A. R. (1996). The somatic marker hypothesis and the possible functions of the prefrontal cortex. Philosophical Transactions of the Royal Society B, 351, 1413–1420. ↩
- James, W. (1884). What is an emotion? Mind, 9(34), 188–205. ↩
- Cannon, W. B. (1927). The James-Lange theory of emotions: a critical examination and an alternative theory. American Journal of Psychology, 39, 106–124. ↩
- Habibi, A., & Damasio, A. (2014). Music, feelings, and the human brain. Psychomusicology, 24(1), 92–102. ↩
- Bechara, A., Damasio, A. R., Damasio, H., & Anderson, S. W. (1994). Insensitivity to future consequences following damage to human prefrontal cortex. Cognition, 50, 7–15. ↩
- Bechara, A., Damasio, H., Tranel, D., & Damasio, A. R. (1997). Deciding advantageously before knowing the advantageous strategy. Science, 275, 1293–1295. ↩
- Maia, T. V., & McClelland, J. L. (2004). A reexamination of the evidence for the somatic marker hypothesis. PNAS, 101(45), 16075–16080. ↩
- Tomb, I., Hauser, M., Deldin, P., & Caramazza, A. (2002). Do somatic markers mediate decisions on the gambling task? Nature Neuroscience, 5, 1103–1104. ↩
- Heims, H. C., Critchley, H. D., Dolan, R., Mathias, C. J., & Cipolotti, L. (2004). Social and motivational functioning is not critically dependent on feedback of autonomic responses. Neuropsychologia, 42, 1979–1988. ↩
- Fellows, L. K., & Farah, M. J. (2005). Different underlying impairments in decision-making following ventromedial and dorsolateral frontal lobe damage in humans. Cerebral Cortex, 15(1), 58–63. ↩
- Lin, C.-H., Chiu, Y.-C., Lee, P.-L., & Hsieh, J.-C. (2007). Is deck B a disadvantageous deck in the Iowa Gambling Task? Behavioral and Brain Functions, 3, 16. ↩
- Steingroever, H., Wetzels, R., Horstmann, A., Neumann, J., & Wagenmakers, E.-J. (2013). Performance of healthy participants on the Iowa Gambling Task. Psychological Assessment, 25(1), 180–193. ↩
- Simonovic, B., Stupple, E., Gale, M., & Sheffield, D. (2019). Sweating the small stuff: a meta-analysis of skin conductance on the Iowa Gambling Task. Cognitive, Affective, & Behavioral Neuroscience, 19, 1097–1112. ↩
- Dunn, B. D., Dalgleish, T., & Lawrence, A. D. (2006). The somatic marker hypothesis: a critical evaluation. Neuroscience & Biobehavioral Reviews, 30, 239–271. ↩
- Damasio, A., & Carvalho, G. B. (2013). The nature of feelings: evolutionary and neurobiological origins. Nature Reviews Neuroscience, 14, 143–152. ↩
- Craig, A. D. (2002). How do you feel? Interoception: the sense of the physiological condition of the body. Nature Reviews Neuroscience, 3, 655–666. ↩
- Damasio, A., Damasio, H., & Tranel, D. (2013). Persistence of feelings and sentience after bilateral damage of the insula. Cerebral Cortex, 23(4), 833–846. ↩
- Barrett, L. F. (2017). The theory of constructed emotion: an active inference account of interoception and categorization. Social Cognitive and Affective Neuroscience, 12(1), 1–23. ↩
- Zamariola, G., Maurage, P., Luminet, O., & Corneille, O. (2018). Interoceptive accuracy scores from the heartbeat counting task are problematic. Biological Psychology, 137, 12–17. ↩
- Man, K., & Damasio, A. (2019). Homeostasis and soft robotics in the design of feeling machines. Nature Machine Intelligence, 1, 446–452. ↩
- Damasio, A. R. (1994). Descartes’ Error: Emotion, Reason, and the Human Brain. Putnam.
The figures, with the gambling task’s schedule as code: articles/damasio.